
A digital state is always a representation of reality. When reality differs, the system must be able to listen.
BestCura / Senior Care · DACH
Senior Care · DACHCare organized around people, not software.
BestCura brings resident state, care planning, documentation, medication, quality, staffing, handovers, inspections and economic evidence into one living work state.
Care first
Technology should carry the complexity.
The surface must stay understandable for professionals even when clinical context, rules, authority, versions and evidence work underneath.

What BestCura can do
A work state instead of a patchwork of modules.
Capabilities are not designed as an isolated feature list. What matters is how an event changes the current state and the work that follows.
Living Clinical Work StateJetzt, als Nächstes, geändert, offen, blockiert und überfällig werden aus dem aktuellen Versorgungskontext abgeleitet.
MD / „MDK“ PrüfbereitschaftQualitätsrelevante Dokumentation, Indikatoren, offene Nachweise und prüfungsrelevante Zustände werden systematisch sichtbar.
Shadow ScoringInterne, nicht offizielle Vorabbewertung auf Basis vorhandener Daten, um mögliche Qualitäts- und Dokumentationslücken vor einer externen Prüfung zu erkennen.
Pflege & eMARPflegedokumentation, Medikation, 5-R-Prüflogik, BTM-nahe Workflows, Wunden, Prophylaxen und Übergaben.
Personal & BetriebDienstplanung, Aufgaben, Qualifikationen, E-Learning, Facility Management, Supply Chain und Management Cockpit.
Document OnceEin klinischer Fakt kann legitime Folgeprozesse aktualisieren, statt mehrfach in getrennten Modulen erfasst zu werden.
Human impact
Less system work. More care.
BestCura should not confront professionals with governance terminology. It should show what changed, what matters, what is open and what can safely happen next.

Under the surface
What users see is the workspace. What runs underneath keeps it coherent.
BestCura deliberately separates a simple working surface from a deterministic clinical foundation. The surface shows people what matters now. The foundation keeps state, context, rules, authority, execution and evidence connected.
BESTCURA SURFACE
Care Flow · Work Dashboard · Clinical Workspace · Management Cockpit · Executive Dashboard
↓
01Clinical StateWhat is currently known?
02Context ResolutionFor whom, where and in which care context?
03Rule ApplicabilityWhich rules apply to this context?
04Authority & ExecutionWho may perform which action?
05Deterministic EvaluationAUTHORIZE · REVIEW · BLOCK
06Evidence & ProvenanceWhat happened, by whom and on what basis?
Evidence changes State.State changes Work.Work changes Care.Care creates new Evidence.
This explains the architectural operating model without disclosing proprietary rule definitions, internal data models, security implementations or execution details.
The Living Clinical Work State
Care Flow turns system complexity into concrete work.
A professional should not have to search through dozens of modules. Care Flow condenses changes, open work, attention, handover and completion into the current working context.
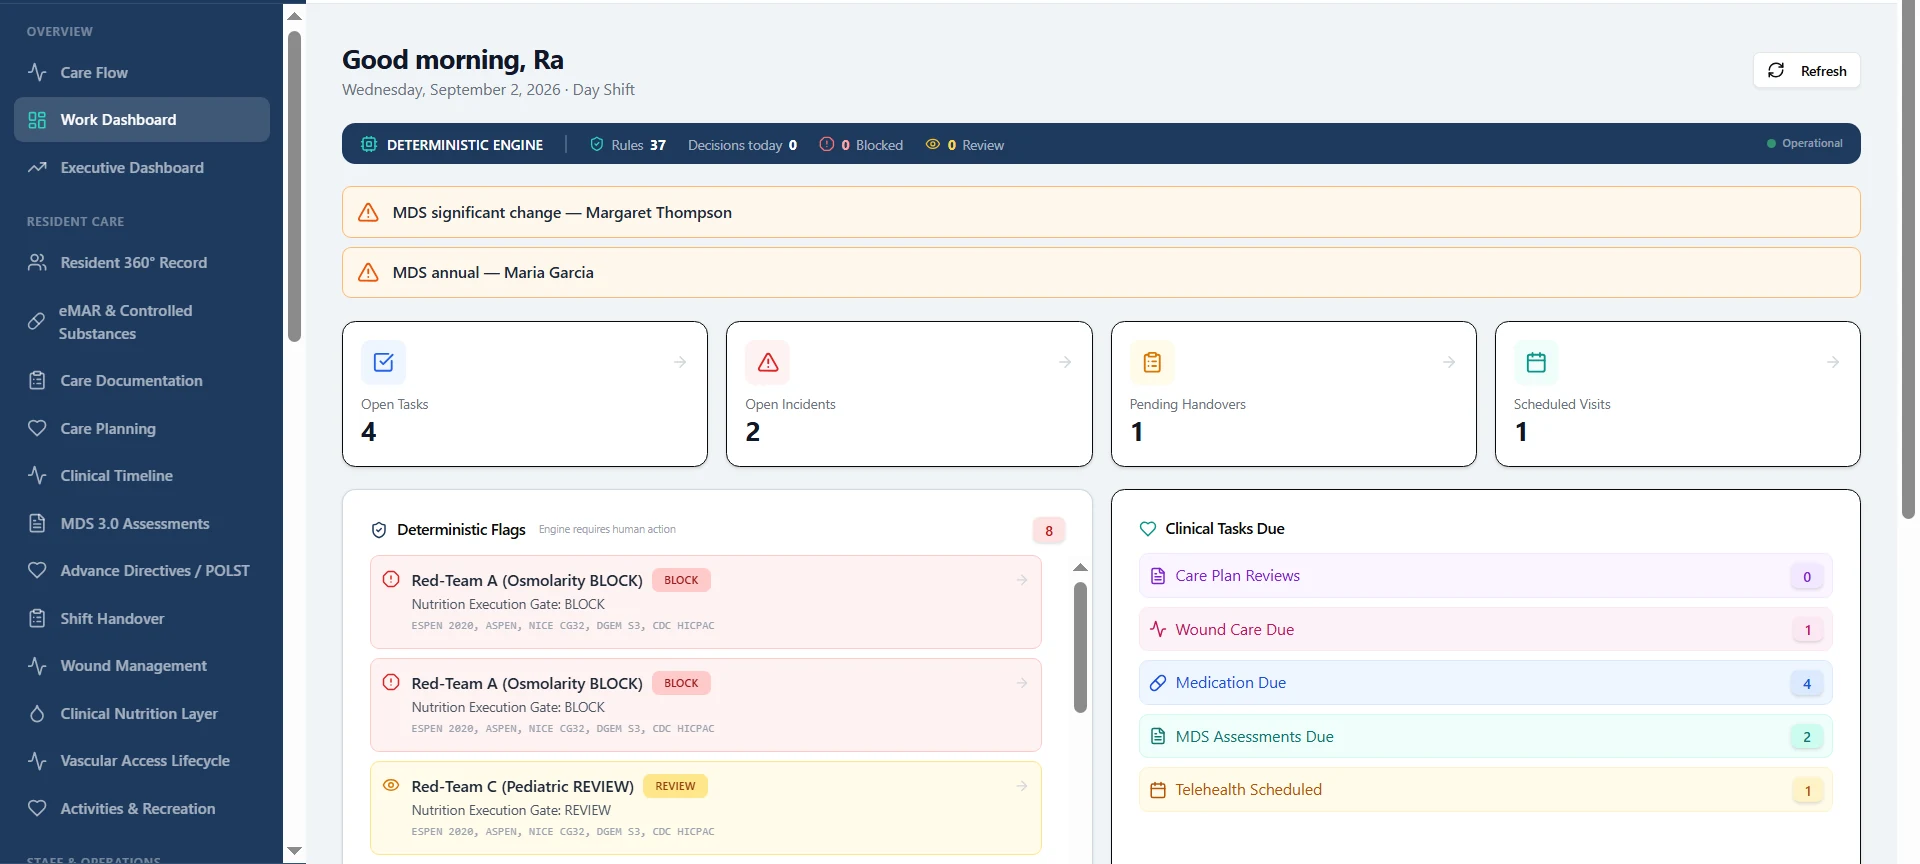
Different role. Same governed state.
The surface changes. The foundation remains.
Nurses, physicians, quality teams and management do not need the same screen. They need different views of a coherent institutional state, with context and authority carried underneath.
NOWATTENTIONCHANGEDWATCHDONE
Executive perspective
Operational care below. Institutional steering above.
Management can see quality, reimbursement integrity, audit readiness, staffing and census without turning those metrics into the source of truth. They are views of the governed state beneath them.
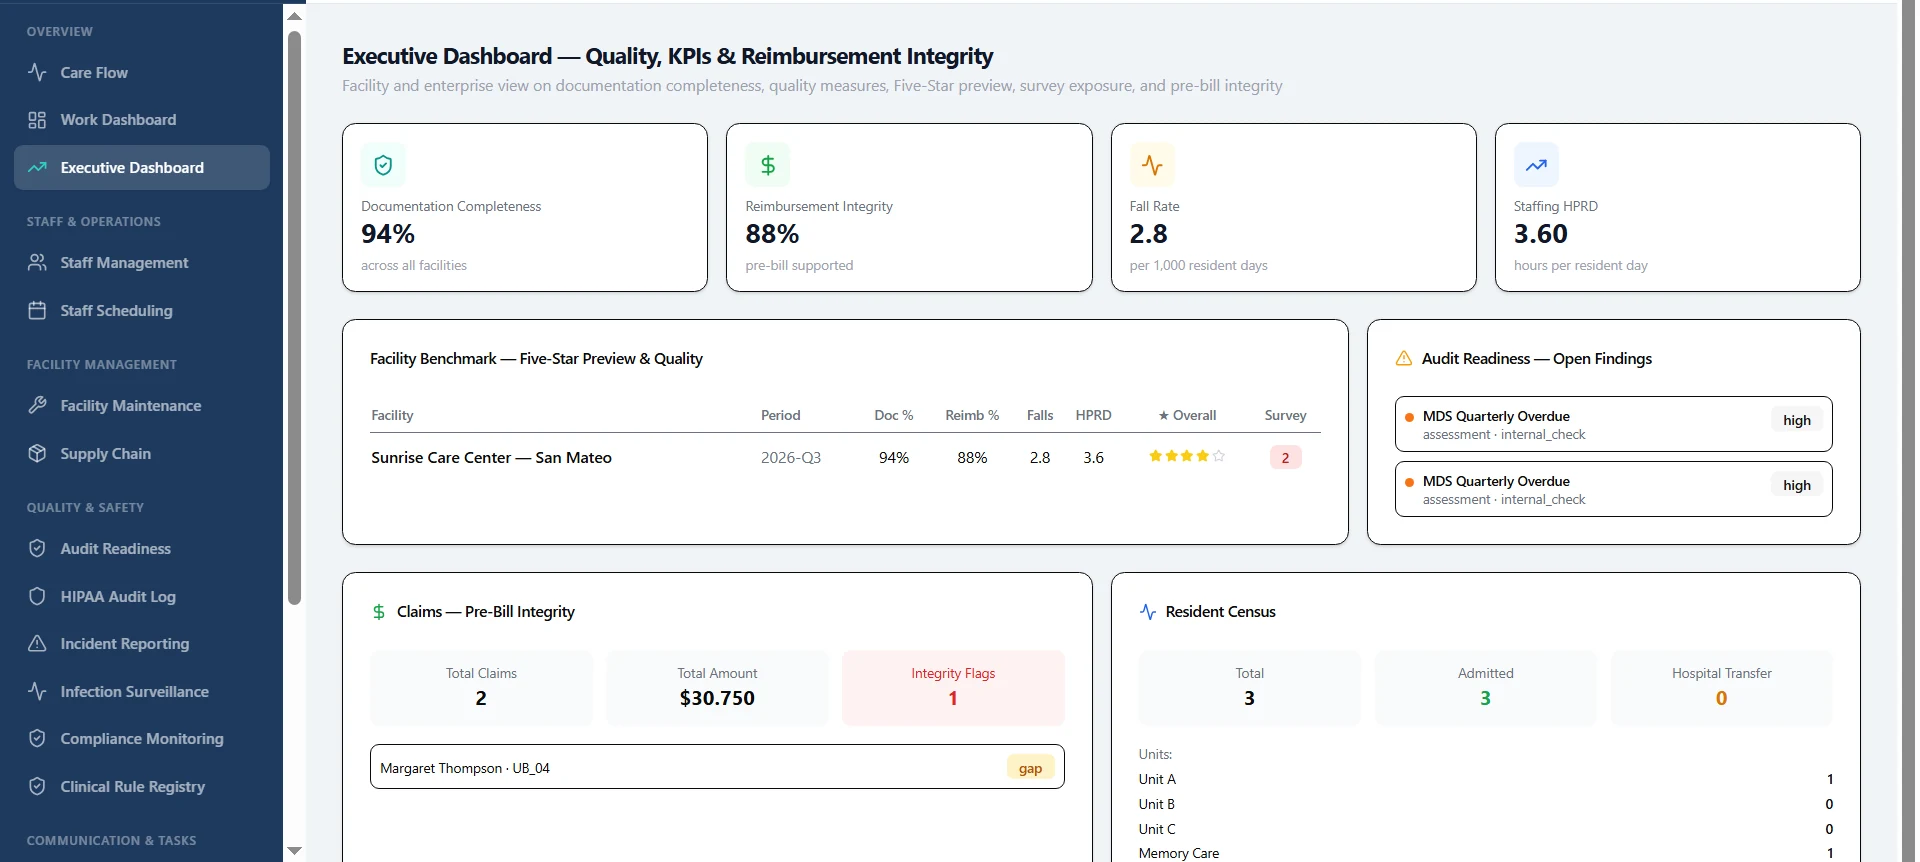
Explore the workspace
DACH nursing home: the real workspace, not a marketing feature list.
Workspace labels below reflect the actual environment supplied for this deployment context. The website explains their role without exposing internal implementation details.
Übersicht3
Care FlowArbeitsmaskeManagement-Cockpit
Bewohnermanagement4
BewohnerHeimplatzverwaltungWartelisteAngehörigenportal
Pflege & Dokumentation6
Einweisung & EntlassÜbergabebuchPflegedokumentationPflegeplanungKI-PflegeberichteOutcome-Tracking
Medizin & Therapie9
MedikamenteMedikamenten-VerifikationÄrztl. AnordnungenWundmanagementParenterale ErnährungClinical Nutrition LayerVascular Access LifecycleClinical Rule RegistryAssessments
Qualität & Compliance15
Predictive Care KIShadow ScoringNBA-AssessmentKI-SturzrisikoPflegebedarf-PrognoseProphylaxePflegegang-ChecklisteMDK-VorbereitungMDK-ComplianceQualitätsmanagementBeschwerdenMPG-BuchIfSG-MeldungenGesetzeskonformitätGesetzesmonitoring
Verwaltung & Finanzen8
Finanz-ControllingEinrichtungenBuchhaltungEnergieanträge KKMaterialwirtschaftInventarVerträgeFahrtenbuch
Hauswirtschaft & Technik4
HauswirtschaftWäscheverzeichnisHaustechnikWartungslisten
Sozialer Dienst2
BetreuungsangeboteAngehörigen-Ansicht
Personal & Schulung4
MitarbeiterDienstplanungKI-SchichtplanungE-Learning
Termine & Aktivitäten2
TermineVeranstaltungen
Kommunikation & Aufgaben3
KommunikationAufgabenVorfälle
Digitale Integration3
ePA-IntegrationTI-AnbindungAAL-Integration
System3
SystemdokuKomplett-HandbuchTenant-Verwaltung
These categories represent the visible product surface. Not every role sees every area.
Regulatory context
Not just document. Work in the right context.
BestCura is not presented as blanket “compliant.” It is designed to bring applicable requirements, professional authority and evidence into context-bound work and execution logic.
SGB XI & QualitätsprüfungBestCura kann Arbeits- und Nachweisprozesse entlang der Qualitätsprüfung in vollstationären Einrichtungen unterstützen.
QPR / QualitätsindikatorenQualitätsindikatoren, Prüfkontext und Qualitätsdarstellung werden als eigene fachliche Zustände behandelt.
DSGVODatenschutz, Rollen, Zweckbindung, Nachvollziehbarkeit und Datenminimierung werden architektonisch berücksichtigt.
IfSG & HygieneInfektionssurveillance und melde-/hygienerelevante Arbeitsprozesse können in den Versorgungszustand eingebunden werden.
Medikation & MedizinprodukteMedikations- und Medizinprodukteprozesse werden kontext- und autoritätsgebunden modelliert.
Einrichtungs- und LandesrechtFacility- und jurisdiktionsspezifische Regeln können versioniert und kontextabhängig angewendet werden.
Note: exact legal and regulatory configuration depends on facility, state/province, care setting, contracts, professional role and deployment.
Traditional systems vs. BestCura
Beyond digital documentation. Care as one connected working state.
The difference is not a prettier screen. It is how the system responds when the reality of care changes.
Core logic
Traditional systemModules and screens
Information lives in separate areas and staff must connect the picture themselves.
BestCuraOne current care and work state
Changes in care update what is relevant, open, changed, or next for the people doing the work.
Documentation
Traditional systemStore entries
Documentation is often the endpoint of a workflow.
BestCuraChanges can create legitimate downstream work
A relevant new fact can update authorized follow-up work, handoffs, and evidence needs.
Safety & authority
Traditional systemRole and access
Access rights often define what a user can do across a module.
BestCuraAccess plus context-bound execution rights
Consequential actions are designed to require the right context, authority, and prerequisites at the point of action.
AI
Traditional systemAssistant or add-on feature
AI generates suggestions, summaries, or alerts.
BestCuraAI informs. Professionals remain responsible.
AI can surface and explain information, but it does not create execution authority by itself.
Audit & evidence
Traditional systemPrepare reports for review
Missing evidence is often discovered during audit preparation.
BestCuraKeep evidence needs visible during operations
Open evidence, relevant states, and gaps are designed to become visible earlier.
Economics
Traditional systemCare and billing are separated
Operational and financial reality are reconstructed across different modules.
BestCuraEconomic representation follows supported care
The financial view is designed to stay connected to care that was actually documented and can be evidenced.
Economic meaning
Care and economics should see the same reality.
Wirtschaftlich zielt BestCura auf weniger Doppeldokumentation, weniger Such- und Übergabezeit, frühere Erkennung fehlender Nachweise, stabilere Prüfvorbereitung und eine sauberere Verbindung zwischen tatsächlich erbrachter Pflege und wirtschaftlicher Abbildung. Shadow Scoring ist dabei kein offizieller MD-Score, sondern ein internes Frühwarn- und Vorbereitungssystem.
In plain language
What BestCura is not trying to be.
Does BestCura replace professionals or clinical responsibility?
No. Rules constrain, AI informs, professionals interpret, execution requires authority, and evidence preserves accountability.
Does BestCura automatically guarantee regulatory compliance?
No. BestCura can support regulatory requirements technically and operationally. Compliance also depends on configuration, operations, organization, contracts and actual use.
HUMAN FIRST · DACHPeople are not records. Care is not a click sequence. Safety must remain human.
In the end, this is not about software. It is about a person.
A resident who wants to be seen, understood and cared for. A family that needs trust. A professional whose attention should not be consumed by screens. BestCura is technically sophisticated so the working day can feel less technical.
Good care grows from relationship, observation, experience and professional responsibility. Technology should carry that work, not displace it.
Rules and authority protect people, but they must be translated into clarity professionals can understand and act on.
AN ORDINARY MOMENT
A small change can mean something very big for one person.
A resident suddenly seems less steady getting up than yesterday. To the nurse or caregiver, that is not a field in a form. It is an observation about a person they know.
BestCura should not turn that moment into bureaucracy. The observation becomes evidence. Care state can change. Affected work becomes visible. Handover carries the change forward. Relevant follow-up can surface for review.
What should the professional see?
Not the machinery underneath. A clear answer: What changed? Why does it matter? What is open? What comes next? What am I authorized to do?
TECHNOLOGY, TRANSLATED INTO HUMAN TERMSClinical State Professional Authority Point-of-Action Revalidation Evidence & Provenance
The Foundation works underneath. People get clarity above it.
“What do we actually know right now?”
Relevant changes stay connected instead of being scattered across separate screens.
For people: less searching, less reconstruction.“Am I authorized to do this here and now?”
A role alone is not the same as execution authority. Context, credential and institutional authority belong together.
For people: clearer boundaries, less uncertainty.“Is that authorization still valid now?”
If something material changes between decision and action, an old state should not silently remain valid.
For people: safety based on the present.“Why did this happen?”
Not just the click. Context, basis and state transition remain part of the trace.
For people: accountability without memory gymnastics.THE ARCHITECTURAL PROMISE
The more complex BestCura becomes underneath, the simpler care should become above it.
We are not building a digital substitute for humanity. We are building an operating environment that carries complexity where people should not have to.
Rules constrain. AI informs. Professionals interpret. Execution requires authority. Humans care for humans.
Talk with us about BestCuraTHE WHOLE INSTITUTION
Care never operates in a vacuum.
Facilities, administration, workforce, care and quality affect one another. BestCura keeps these domains in one tenant-based institutional context without collapsing role or access boundaries.